


Treatment considerations
Considering treatment after MAC lung disease is identified
When MAC lung disease progression is identified, it's important to reassess treatment plans1
The following factors are associated with relatively poor prognosis in MAC lung disease:
- •Positive AFB sputum smears
- •Cavitary disease
- •Underlying immunosuppression
- •Low BMI, low albumin, and/or elevated inflammatory markers
- •Major symptoms diminishing quality of life such as severe fatigue
Consider initiating multidrug therapy if patients exhibit these factors.
Before starting treatment, discuss the patient’s symptoms, preferences, and ability to undergo therapy1,2
Components to consider as part of the overall plan include2:
- •Bronchodilators
- •Smoking cessation
- •Airway clearance
- •Nutrition
- •Exercise and cardiovascular fitness
After an evaluation of all risks and benefits and the goals of therapy, active monitoring may be considered when immediate treatment with antibiotics is not the preferred option.1
The NTM Guidelines state that early consideration of multidrug therapy is warranted when treating MAC lung disease1
Starting multidrug therapy may significantly improve respiratory symptoms at 3 and 6 months3
A randomized, multisite, pragmatic clinical trial of patients treated with multidrug therapy (azithromycin-based 2-drug or 3-drug therapy) found respiratory symptom improvement at Months 3 and 6 in 144 of 228 patients with MAC lung disease who completed longitudinal surveys.3

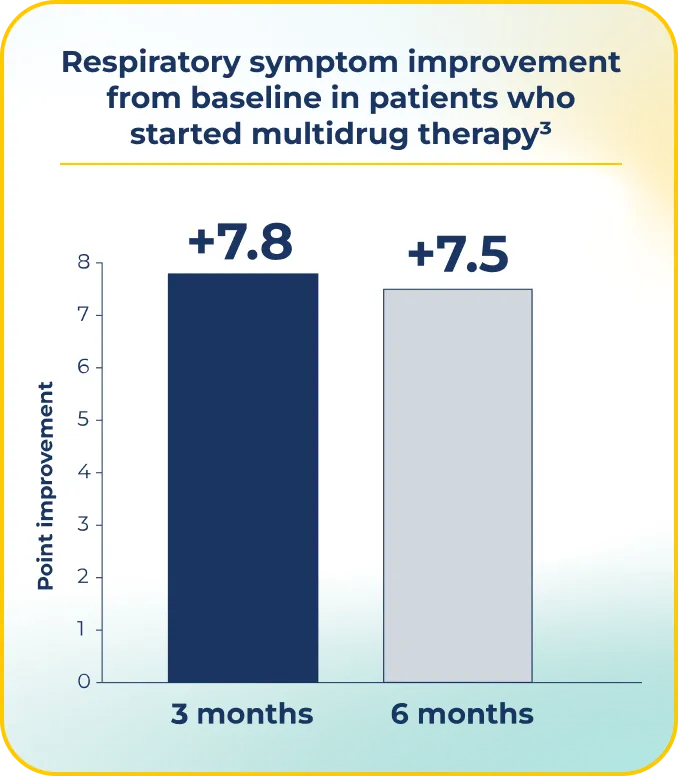
At 3 and 6 months of multidrug therapy use, the clinical trial found3:
- •Based on surveys, respiratory symptoms improved by 7.8 points (P<0.001) and 7.5 points (P<0.001)
- -This was greater than the minimally important difference of 6.4 points to 6.9 points
- •Improved respiratory symptoms were seen in as few as 3 months after starting multidrug therapy
90% of patients studied had comorbid bronchiectasis.3
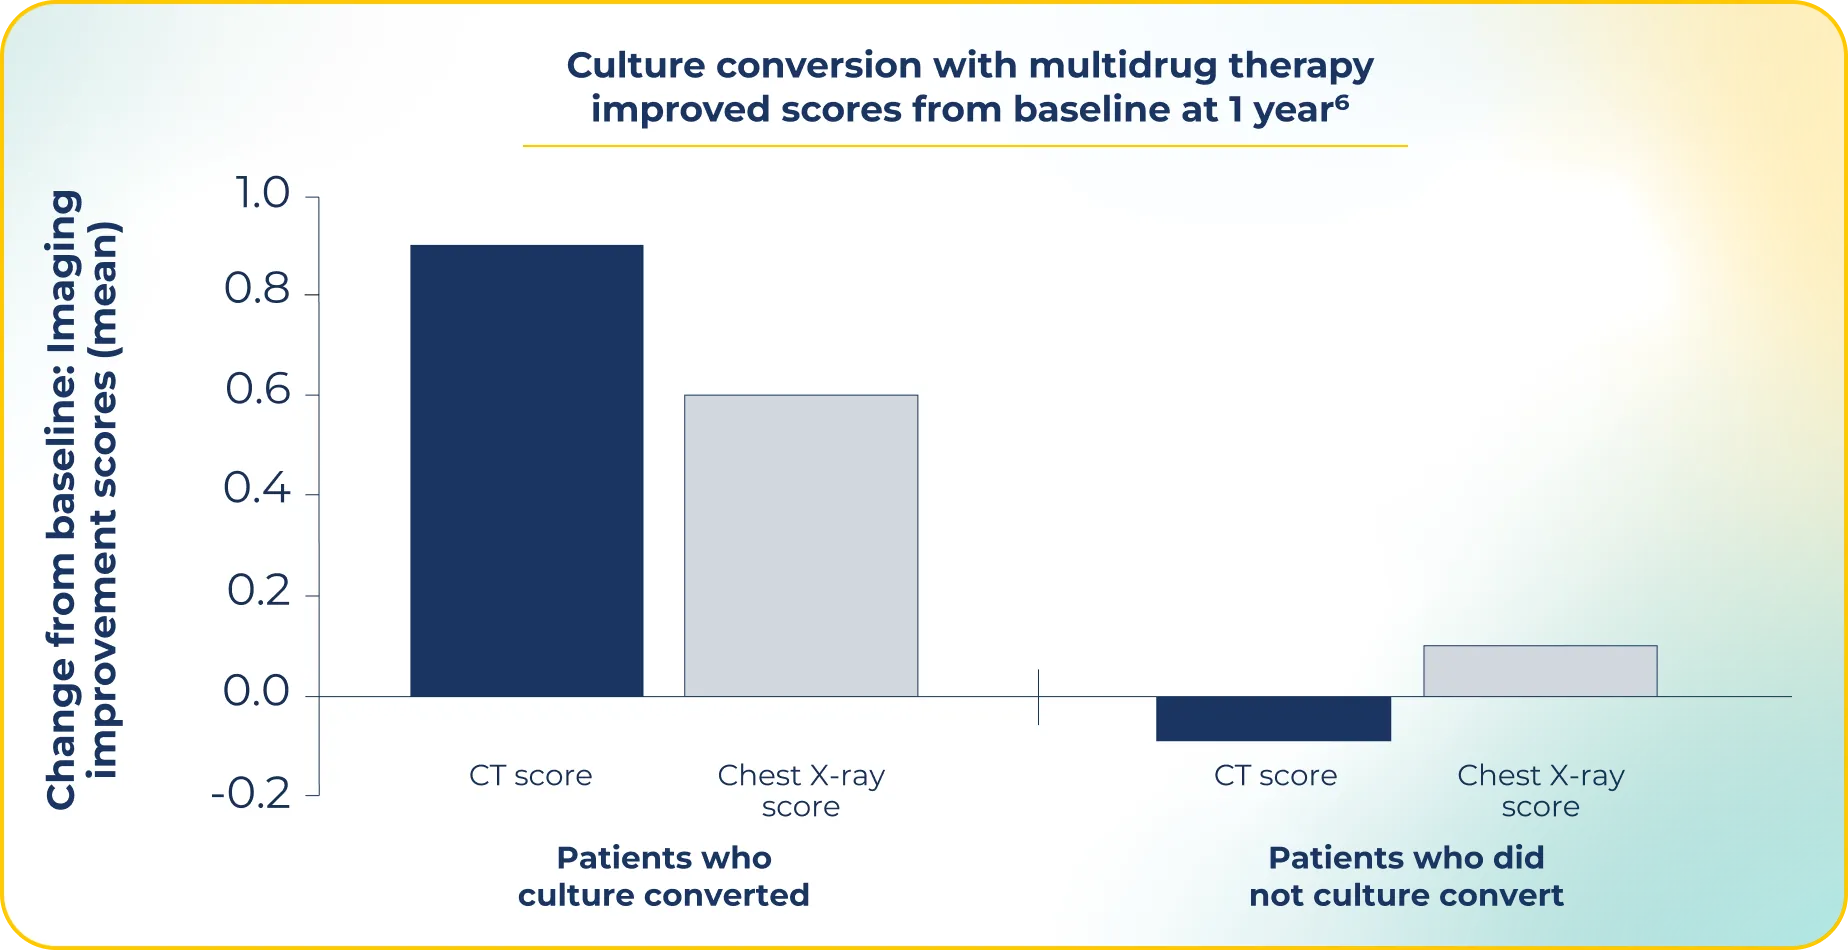
Culture conversion with multidrug therapy may lead to radiologic improvement4,5
In a retrospective, observational cohort study of patients with nodular/bronchiectatic MAC lung disease treated with standard macrolide-containing multidrug regimens, patients who culture converted (n=148/180) had significantly greater radiologic improvement from baseline (P<0.0001) vs nonconverters (n=32/180) in both CT scans and chest X-rays. Culture score improvements were also significantly associated with radiologic improvement, with a stronger association observed for CT scans than chest X-rays.6
Earlier use of multidrug therapy (≤3 months following diagnosis) significantly reduced respiratory-related hospitalizations4
A 2-year retrospective observational cohort study of insurance claims data for patients who received early (n=364/481) or delayed (n=117/481) antibiotic treatment initiation for NTM lung disease showed a significant reduction in respiratory-related hospitalizations vs baseline.4
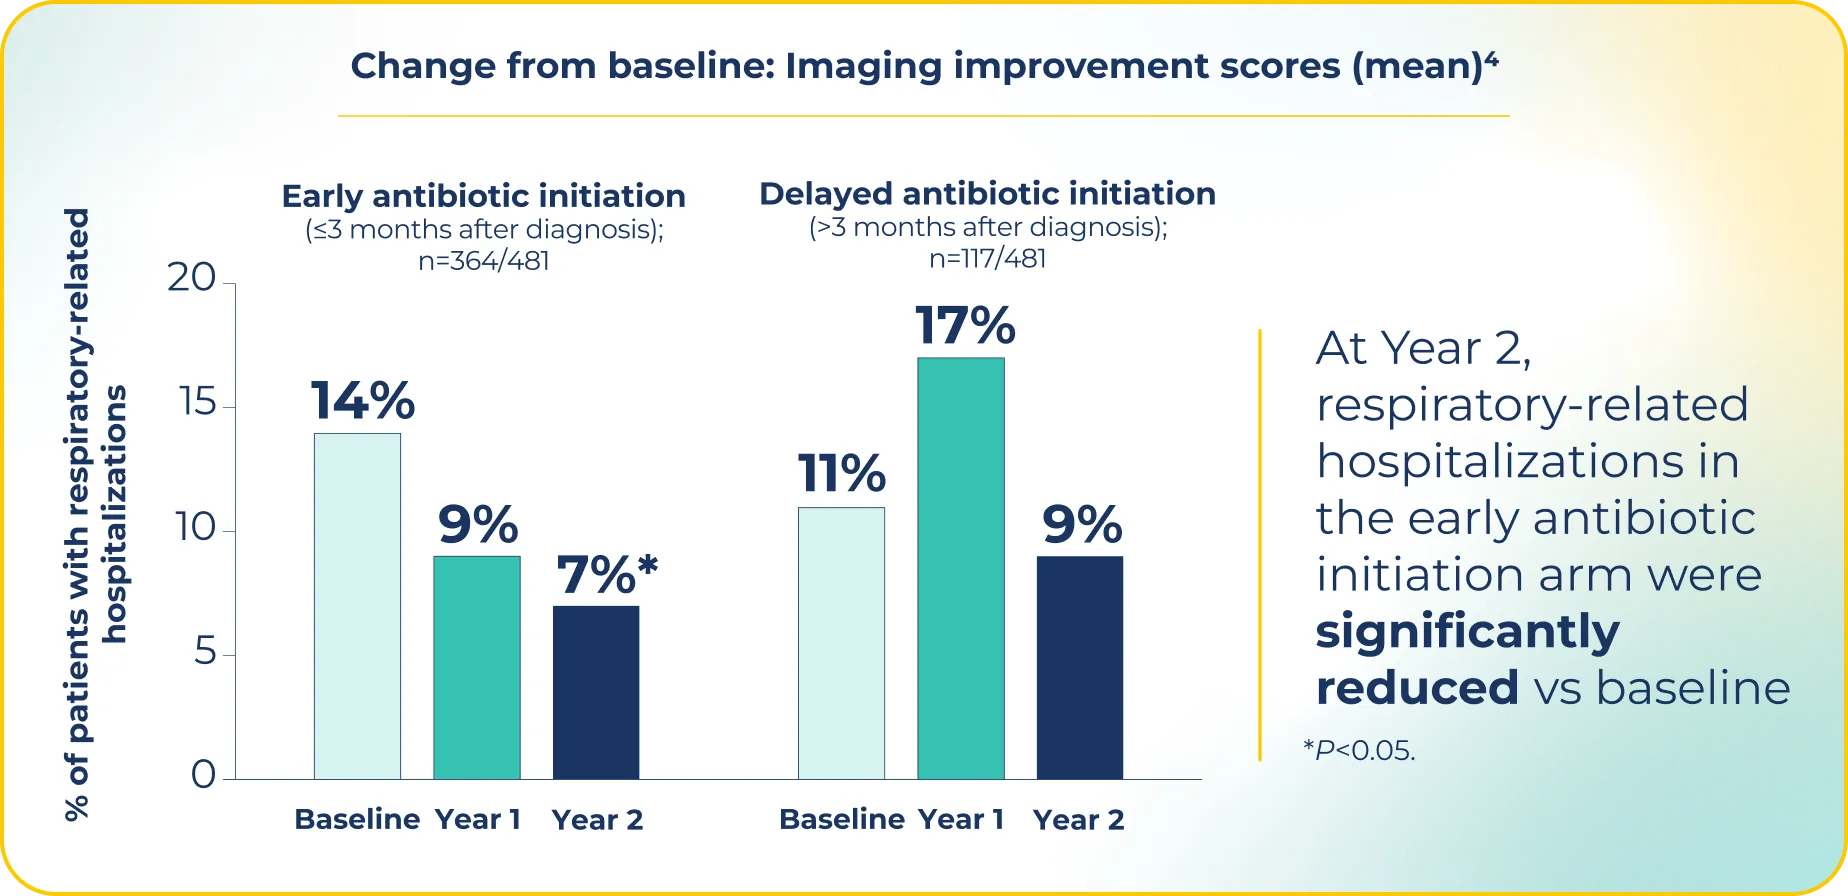
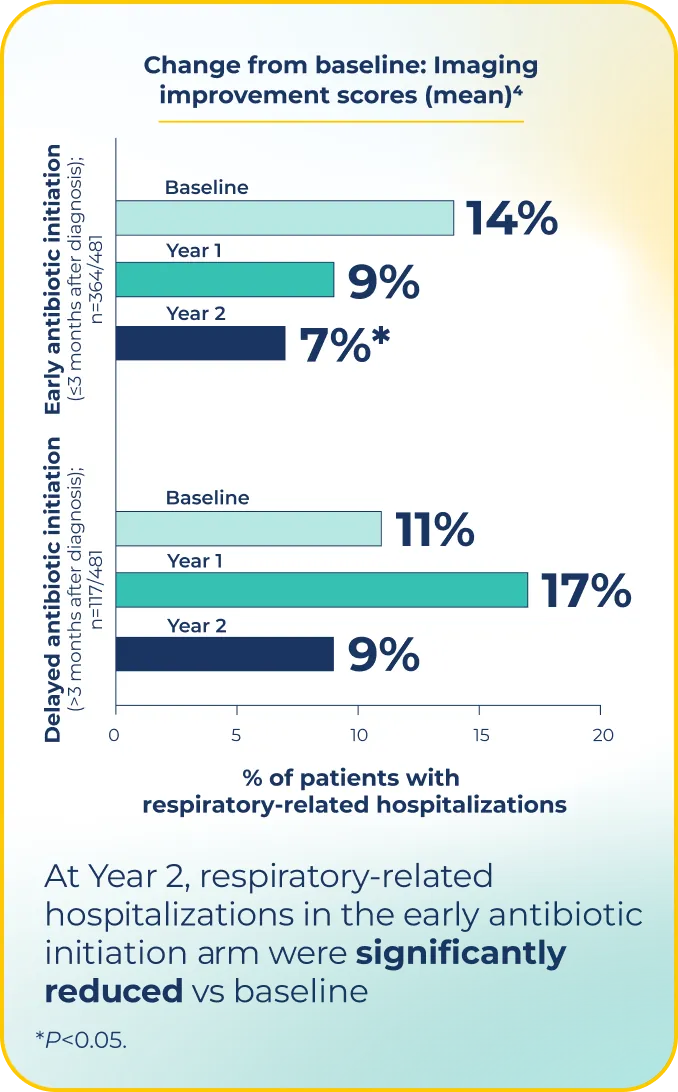
No significant changes from baseline in respiratory-related hospitalizations were seen at Years 1 and 2 in those who received delayed antibiotic treatment.4
Individualizing monitoring frequency
Monitor for adverse drug reactions routinely, as side effects and intolerance can be common with multidrug therapy regimens. According to the 2020 NTM Guidelines, it’s important to individualize the frequency of monitoring for adverse reactions based on patient age, comorbidities, concurrent drugs, and overlapping drug toxicities.1,2,7
- •Some medications may need to be introduced gradually at 1- to 2-week intervals so that appropriate evaluations of tolerance can be performed2
Depending on the antibiotics selected, there may be a need to refer to other specialists for routine monitoring, including an2:
- •Ophthalmologist for vision testing
- •Audiologist to perform baseline audiograms and hearing tests
It’s important to review each patient's medication list before starting treatment, and to monitor for potential interactions throughout the treatment period.2,7
Once a treatment plan is in place, setting expectations is important
Treatment for MAC lung disease can be challenging, so when initiating treatment, setting expectations for patients is critical for appropriate management. It's important to discuss length of therapy, treatment response, follow-up appointments, and potential adverse events with patients.1,7-9
Discussing what to expect with patients may help them complete treatment as prescribed2,8

Encourage patients to prepare for their visits using this conversation starter.
Setting expectations for your patients can help them feel more prepared for their treatment journey

Review MAC lung disease resources
AFB=acid-fast bacilli; BMI=body mass index; CI=confidence interval; CT=computed tomography; NTM=nontuberculous mycobacteria; OR=odds ratio.
References: 1. Daley CL, Iaccarino JM, Lange C, et al. Treatment of nontuberculous mycobacterial pulmonary disease: an official ATS/ERS/ESCMID/IDSA clinical practice guideline. Clin Infect Dis. 2020;71(4):e1-e36. doi:10.1093/cid/ciaa241 2. Griffith DE, Aksamit T, Brown-Elliott BA, et al; ATS Mycobacterial Diseases Subcommittee. An official ATS/IDSA statement: diagnosis, treatment, and prevention of nontuberculous mycobacterial diseases. Am J Respir Crit Care Med. 2007;175(4):367-416. doi:10.1164/rccm.200604-571ST 3. Henkle E, Quittner AL, Dieckmann NF, et al. Patient-reported symptom and health-related quality-of-life validation and responsiveness during the first 6 months of treatment for Mycobacterium avium complex pulmonary disease. Chest. 2023;164(1):53-64. doi:10.1016/j.chest.2023.02.015 4. Winthrop K, Waweru C, Hassan M, et al. Reductions in hospitalisations and emergency department visits with early antibiotic initiation in nontuberculous mycobacterial lung disease. ERJ Open Res. 2024;10(4):1-11. doi:10.1183/23120541.00963-2023 5. Lee G, Kim HS, Lee KS, et al. Serial CT findings of nodular bronchiectatic Mycobacterium avium complex pulmonary disease with antibiotic treatment. AJR Am J Roentgenol. 2013;201(4):764-772. doi:10.2214/AJR.12.9897 6. Griffith DE, Adjemian J, Brown-Elliott BA, et al. Semiquantitative culture analysis during therapy for Mycobacterium avium complex lung disease. Am J Respir Crit Care Med. 2015;192(6):754-760. doi:10.1164/rccm.201503-0444OC 7. Ryu YJ, Koh WJ, Daley CL. Diagnosis and treatment of nontuberculous mycobacterial lung disease: clinicians' perspectives. Tuberc Respir Dis (Seoul). 2016;79(2):74-84. doi:10.4046/trd.2016.79.2.74 8. Griffith DE, Aksamit TR. Therapy of refractory nontuberculous mycobacterial lung disease. Curr Opin Infect Dis. 2012;25(2):218-227. doi:10.1097/QCO.0b013e3283511a64 9. Adjemian J, Prevots DR, Gallagher J, Heap K, Gupta R, Griffith D. Lack of adherence to evidence-based treatment guidelines for nontuberculous mycobacterial lung disease. Ann Am Thorac Soc. 2014;11(1):9-16. doi:10.1513/AnnalsATS.201304-085OC